

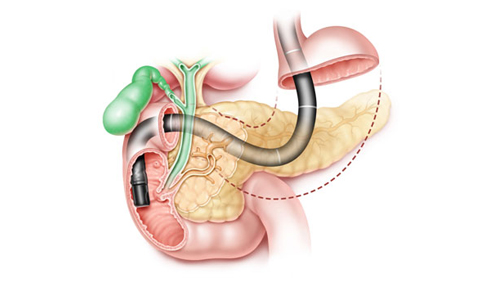
Difficult ERCPs
Difficult ERCPs are advanced endoscopic procedures performed when routine access to or treatment of the bile or pancreatic ducts is challenging. Specialized techniques and accessories may be required for complex stone removal, ductal dilatation, stent placement or other therapeutic interventions.
Endoscopic Retrograde Cholangiopancreatography (ERCP) is used for the diagnosis and treatment of disorders involving the biliary and pancreatic ducts. Some cases can be technically challenging because of difficult duct access, altered anatomy, large or impacted stones, strictures or previous interventions.
Dr. Suresh H. Pasiddhi has documented expertise in difficult ERCPs, including biliary and pancreatic interventions, difficult stone or stent management and advanced ductal procedures.
Conditions
Difficult ERCPs may be required for complex biliary and pancreatic conditions, including:
- Large, multiple or difficult common bile duct stones
- Pancreatic duct stones requiring advanced endoscopic treatment
- Complex biliary strictures and narrowing
- Pancreatic duct strictures
- Blocked, migrated or difficult-to-remove biliary stents
- Blocked or migrated pancreatic duct stents
- Persistent biliary or pancreatic duct obstruction
- Complex ductal conditions following previous procedures
Symptoms
Symptoms that may lead to evaluation and therapeutic ERCP include:
Biliary Symptoms
- Jaundice or yellowing of the eyes and skin
- Upper abdominal or right-sided abdominal pain
- Dark urine or pale stools
- Itching related to impaired bile drainage
- Fever or chills when biliary infection is present
Pancreatic Symptoms
- Upper abdominal pain, sometimes radiating to the back
- Recurrent episodes of pancreatitis
- Nausea or vomiting
- Persistent or recurrent abdominal discomfort
- Symptoms related to an underlying pancreatic duct disorder
Causes
ERCP may become technically difficult because of several factors, depending on the individual patient and the underlying condition:
- Large, impacted or multiple bile duct stones
- Narrowing or distortion of the bile or pancreatic ducts
- Inflammation and scarring associated with chronic pancreatitis
- Previous ERCP or biliary and pancreatic procedures
- Altered gastrointestinal anatomy following surgery
- Complex biliary or pancreatic obstruction
Treatment
Difficult ERCPs are performed using advanced endoscopic and fluoroscopic techniques under appropriate sedation or anesthesia. The approach is selected according to the patient's anatomy, the nature of the obstruction and the intended treatment.
Depending on the findings, advanced ERCP treatment may include:
- Advanced guidewire-assisted biliary or pancreatic duct cannulation
- Removal of difficult CBD stones using balloons, baskets and specialized accessories
- Pancreatic duct stone removal in selected cases
- Endoscopic sphincterotomy when clinically appropriate
- Dilatation of selected biliary or pancreatic duct strictures
- Biliary and pancreatic stent placement, removal or exchange
- Management of complex ductal obstruction using advanced ERCP techniques
Some complex ERCPs may require staged treatment or additional advanced endoscopic or other intervention when complete treatment cannot be safely achieved in a single session.
Prevention & Follow-Up
Careful follow-up after a difficult ERCP is important, particularly when a stent has been placed or further treatment is planned.
Helpful measures include:
- Follow the recommended treatment plan for the underlying biliary or pancreatic condition.
- Attend scheduled follow-up appointments after the procedure.
- Complete recommended blood tests or imaging when advised.
- Keep scheduled appointments for stent removal or exchange when required.
- Follow prescribed medicines and post-procedure dietary instructions.
- Seek prompt medical attention for severe or worsening abdominal pain, fever, jaundice, persistent vomiting or other concerning symptoms after ERCP.
The need for further treatment depends on the underlying disease, procedural findings and response to treatment. Regular follow-up helps ensure effective ductal drainage and timely management of any remaining or recurrent obstruction.